
Tips
ADHD Brain vs Normal Brain: 6 Key Differences
ADHD Brain vs Normal Brain: 6 Key Differences

Is the ADHD Brain Actually Different?
Yes -- and that's not a metaphor. Decades of neuroimaging research confirm that the ADHD brain vs normal brain comparison reveals measurable structural and functional differences. These are not subtle. Brain scans show reduced volume in specific regions, altered network connectivity, and distinct dopamine signaling patterns in people with ADHD compared to neurotypical individuals.
This matters beyond the academic. When people understand that ADHD reflects real neurological differences, it changes how they approach treatment, accommodation, and self-understanding. ADHD is not a preference, a lifestyle, or a failure of effort. It is a brain that is built and wired differently.
Here are six of the most well-documented differences between the ADHD brain and the neurotypical brain, drawn from peer-reviewed research.
Key Takeaways
The ADHD brain shows reduced volume in regions governing executive function and impulse control, with development running roughly 2-3 years behind neurotypical peers in childhood.
The dopamine system works differently in ADHD, producing lower motivation signals for routine tasks and driving the brain toward high-stimulation seeking behavior.
Structural differences don't disappear in adulthood, but the brain adapts -- and the right external structure can compensate for what the ADHD brain doesn't do automatically.
Difference 1: Prefrontal Cortex Volume and Maturation
The prefrontal cortex (PFC) governs planning, impulse control, working memory, and the ability to think before acting. In ADHD brains, the PFC shows reduced gray matter volume and matures significantly later than in neurotypical peers.
A landmark 2007 study published in PNAS found that cortical maturation in children with ADHD lagged neurotypical peers by an average of 2-3 years, with the delay most pronounced in the PFC. The "peak thickness" in the prefrontal regions arrived years later -- meaning the biological system that manages impulse control was, quite literally, not yet online when neurotypical children were already developing it.
This is why ADHD children are often described as immature relative to peers. They're not being difficult. Their prefrontal development is genuinely behind. For many adults, this catch-up continues into the mid-20s.
Difference 2: Dopamine Signaling and Reward Processing
The ADHD brain has fewer dopamine transporters and reduced dopamine receptor density in the striatum and prefrontal cortex. This means that ordinary tasks -- the kind that provide just enough dopamine to motivate neurotypical people -- simply don't generate a sufficient signal in ADHD brains.
This is the neurological explanation for why tasks feel impossible until they have a deadline, why ADHD people can hyperfocus on genuinely interesting work but can't start something routine. The reward signal is too weak to trigger engagement unless the task provides substantial dopamine input through novelty, urgency, or personal interest.
Stimulant medications work by increasing dopamine availability. This isn't giving the ADHD brain an unfair advantage -- it's restoring it closer to the baseline that neurotypical brains operate at naturally. For more on this mechanism, see our guide to ADHD and dopamine deficits.
Difference 3: Default Mode Network Suppression
The default mode network (DMN) is the brain's "resting state" -- a network active during mind-wandering, self-referential thinking, and daydreaming. In neurotypical brains, the DMN quiets down when a task requires focused attention. The cognitive control network takes over, and the mind stays on task.
In ADHD brains, this suppression is impaired. The DMN fails to quiet when it should, competing with attentional networks rather than standing down. This is the neurological basis of mind-wandering during tasks, internal distraction, and the sense that the brain is "hijacked" mid-task by unrelated thoughts.
Research using fMRI has shown that the degree of DMN suppression failure correlates with symptom severity in ADHD. The more the DMN stays active during tasks, the more attention problems are reported. This finding also explains why high-stimulation environments (noise, visual complexity, interesting context) can paradoxically help some ADHD people -- the external stimulation competes with the wandering DMN and keeps executive networks more engaged.
Difference 4: Smaller Basal Ganglia and Cerebellum
Multiple neuroimaging studies have identified reduced volume in the basal ganglia, particularly the caudate nucleus, in people with ADHD. The basal ganglia play a central role in motor control, procedural learning, and the selection of actions based on past experience -- in short, habit formation and automatic behavior.
When the basal ganglia are underactive, things that should become automatic -- routines, habits, social scripts -- require more conscious effort. This is why maintaining consistent habits is disproportionately hard for people with ADHD. The brain region that normally automates those behaviors runs at a reduced capacity.
The cerebellum, which controls timing and motor coordination but also contributes to cognitive timing and attention shifting, also shows reduced volume in some ADHD neuroimaging studies. This may contribute to the time perception difficulties and "time blindness" that many people with ADHD experience acutely.
Difference 5: Altered Connectivity Between Networks
Beyond individual brain regions, the connections between regions -- measured via resting-state fMRI -- show meaningful differences in ADHD. The communication between the executive control network and regions involved in salience detection (which things to pay attention to) is weaker. The prefrontal cortex exerts less top-down control over automatic responses.
This altered connectivity helps explain why ADHD involves more than just attention problems. Emotional dysregulation, impulsivity, working memory failures, and difficulty shifting between tasks all trace back to this broad connectivity pattern. For more on the emotional side, see our deep-dive on emotional dysregulation in ADHD.
Importantly, some connectivity differences become less pronounced with age and treatment, suggesting the brain retains meaningful plasticity in these networks.
Difference 6: Norepinephrine and the Arousal System
The ADHD brain also shows differences in norepinephrine signaling, particularly in the locus coeruleus -- the brain's main source of norepinephrine, which regulates arousal, alertness, and the ability to filter relevant from irrelevant input.
In neurotypical brains, optimal norepinephrine levels create a state of focused alertness. Too little produces inattention and difficulty filtering noise. The ADHD brain tends to run at suboptimal norepinephrine levels under ordinary conditions, which is why non-stimulant ADHD medications like atomoxetine and guanfacine target the norepinephrine system rather than dopamine directly.
This also explains why ADHD brains struggle with tasks in quiet environments. Without adequate arousal signal, the brain doesn't distinguish important from unimportant stimuli well. External stimulation -- noise, movement, a change of scene -- can paradoxically improve focus by raising arousal to a more functional level.
What This Means for Daily Life
Understanding the structural and chemical differences in the ADHD brain matters because it points toward strategies that actually work. Trying harder at the things the brain does poorly generates frustration and failure. Working with the brain's profile gets results.
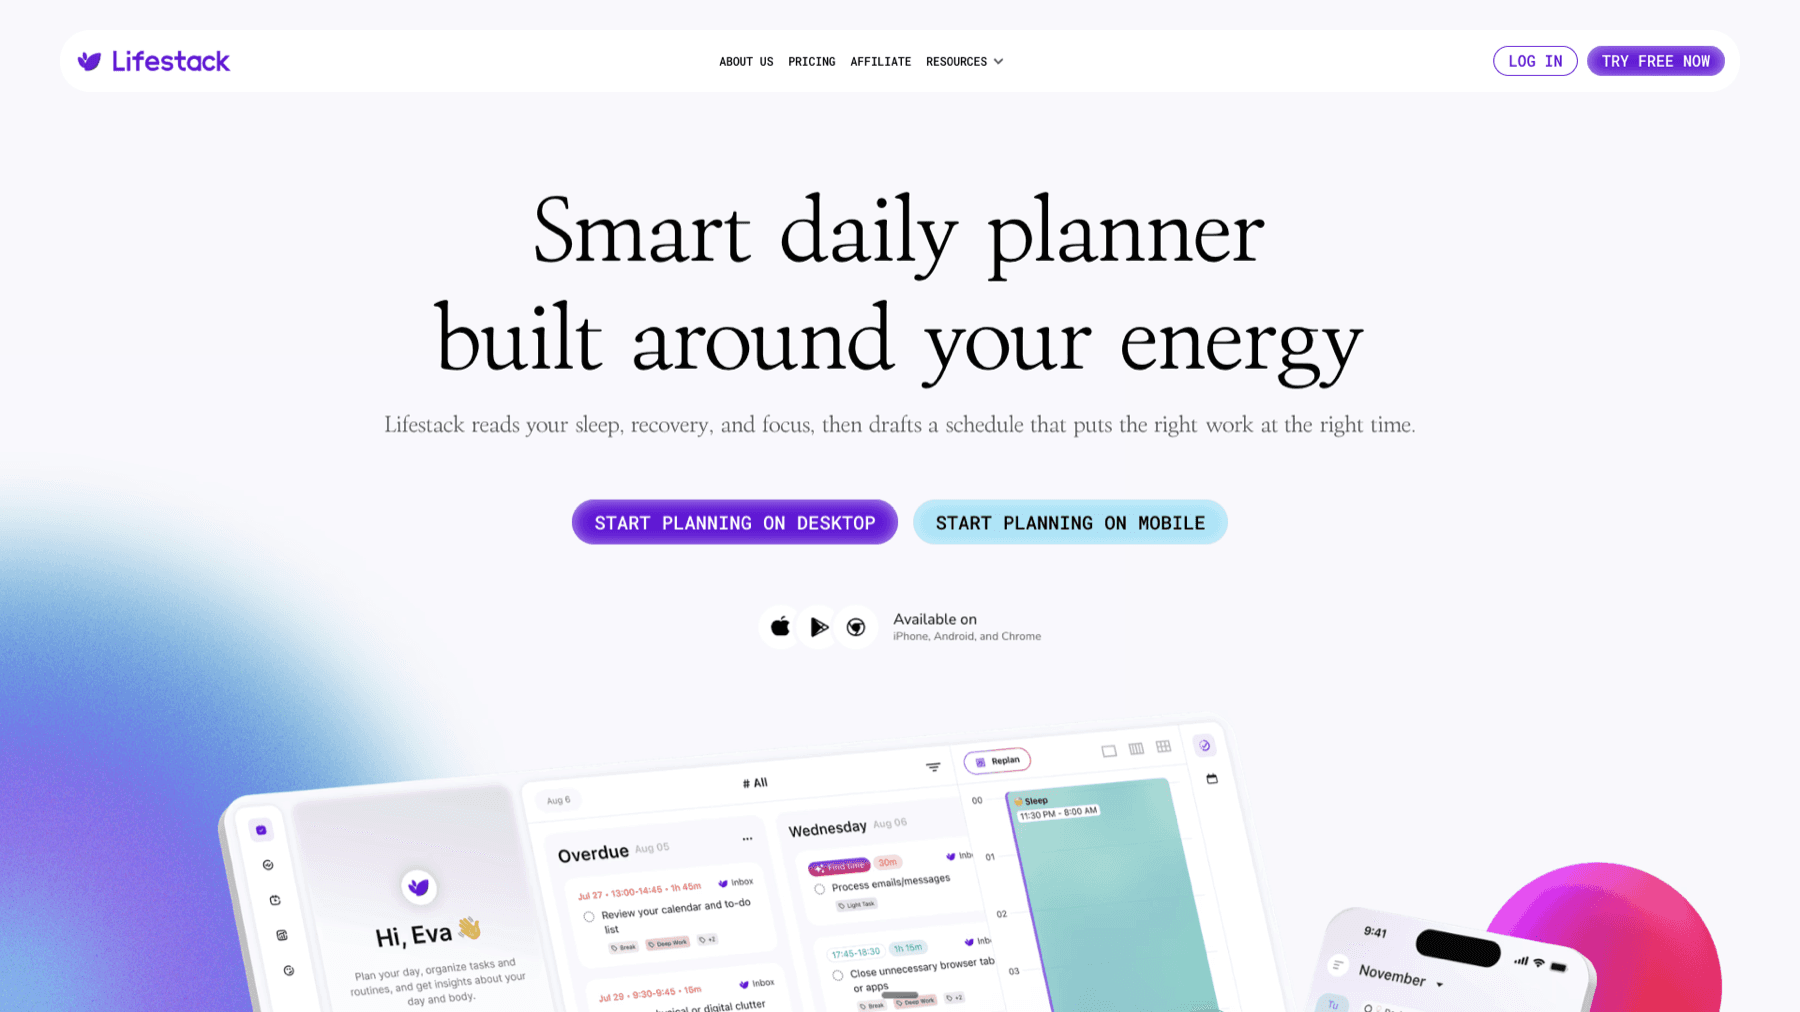
One of the most practical implications involves scheduling. The ADHD brain has a narrower window of peak dopamine and norepinephrine availability -- typically shorter and less predictable than neurotypical brains. Stacking demanding cognitive work into that window and protecting it from interruption produces significantly better outcomes than spreading work evenly across the day.
Lifestack automates this by scheduling tasks based on your energy pattern rather than calendar slots. It places high-focus work in your peak window, low-demand tasks when you're running on fumes. For a brain that can't reliably perform this optimization manually -- because the PFC is busy just managing moment-to-moment demands -- an external system that does it automatically is not a luxury. It's compensation for a real structural difference.
Combined with consistent sleep, exercise, and an ADHD morning routine, energy-aware scheduling gives the ADHD brain the external scaffolding that the neurotypical brain handles internally.
Best Tool for Supporting the ADHD Brain
The structural differences in the ADHD brain don't disappear, but they can be compensated for with the right systems. Lifestack is built for exactly this: its energy-aware AI scheduler compensates for the ADHD brain's impaired self-scheduling ability by automatically placing tasks where they're most likely to get done.
Where the neurotypical brain can intuitively sequence a workday, the ADHD brain often stalls at exactly that planning step. Lifestack removes the step entirely -- giving you a ready schedule that accounts for deadlines, energy, and priority so you can get into work instead of preparing to work. At $7/month or $50/year with a 7-day free trial, it's one of the most focused ADHD-aligned planning tools available.
Frequently Asked Questions
What is the main difference between the ADHD brain and a normal brain?
The most consistently documented differences are: reduced prefrontal cortex volume and maturation, lower dopamine receptor density, impaired default mode network suppression during tasks, and reduced basal ganglia volume. These together produce the attention, motivation, and impulse control difficulties characteristic of ADHD.
Does the ADHD brain look different on a scan?
Yes, in group studies. MRI and fMRI studies consistently find structural and connectivity differences in ADHD brains compared to neurotypical controls. Individual scans aren't diagnostic -- the differences show up at the population level, not reliably enough to diagnose a single person from a scan alone.
Do ADHD brain differences go away in adulthood?
Not entirely. The prefrontal cortex continues maturing through the mid-20s, and some differences become less pronounced. But core structural differences in the basal ganglia, dopamine system, and connectivity patterns persist into adulthood. Approximately 60-75% of children with ADHD continue to meet diagnostic criteria as adults.
Is the ADHD brain smarter or more creative?
The ADHD brain is not uniformly smarter or more creative -- it's differently wired. Some ADHD traits (divergent thinking, high curiosity, hyperfocus capacity) can support creativity. Others (working memory deficits, attention regulation) can impair it. The relationship varies by individual and domain.
What helps the ADHD brain function better?
A combination of medication (stimulants or non-stimulants targeting dopamine and norepinephrine), behavioral strategies, adequate sleep, focus strategies, and external structure. Tools that compensate for planning and self-organization deficits -- like energy-aware schedulers -- directly address the functional gaps created by prefrontal and basal ganglia differences.
Can the ADHD brain change with treatment?
Yes. Stimulant medication produces measurable changes in prefrontal activity and connectivity during treatment. Long-term behavioral interventions and CBT for ADHD also support neuroplastic adaptation. The brain doesn't become neurotypical, but it adapts to use available capacity more effectively.
Is the ADHD Brain Actually Different?
Yes -- and that's not a metaphor. Decades of neuroimaging research confirm that the ADHD brain vs normal brain comparison reveals measurable structural and functional differences. These are not subtle. Brain scans show reduced volume in specific regions, altered network connectivity, and distinct dopamine signaling patterns in people with ADHD compared to neurotypical individuals.
This matters beyond the academic. When people understand that ADHD reflects real neurological differences, it changes how they approach treatment, accommodation, and self-understanding. ADHD is not a preference, a lifestyle, or a failure of effort. It is a brain that is built and wired differently.
Here are six of the most well-documented differences between the ADHD brain and the neurotypical brain, drawn from peer-reviewed research.
Key Takeaways
The ADHD brain shows reduced volume in regions governing executive function and impulse control, with development running roughly 2-3 years behind neurotypical peers in childhood.
The dopamine system works differently in ADHD, producing lower motivation signals for routine tasks and driving the brain toward high-stimulation seeking behavior.
Structural differences don't disappear in adulthood, but the brain adapts -- and the right external structure can compensate for what the ADHD brain doesn't do automatically.
Difference 1: Prefrontal Cortex Volume and Maturation
The prefrontal cortex (PFC) governs planning, impulse control, working memory, and the ability to think before acting. In ADHD brains, the PFC shows reduced gray matter volume and matures significantly later than in neurotypical peers.
A landmark 2007 study published in PNAS found that cortical maturation in children with ADHD lagged neurotypical peers by an average of 2-3 years, with the delay most pronounced in the PFC. The "peak thickness" in the prefrontal regions arrived years later -- meaning the biological system that manages impulse control was, quite literally, not yet online when neurotypical children were already developing it.
This is why ADHD children are often described as immature relative to peers. They're not being difficult. Their prefrontal development is genuinely behind. For many adults, this catch-up continues into the mid-20s.
Difference 2: Dopamine Signaling and Reward Processing
The ADHD brain has fewer dopamine transporters and reduced dopamine receptor density in the striatum and prefrontal cortex. This means that ordinary tasks -- the kind that provide just enough dopamine to motivate neurotypical people -- simply don't generate a sufficient signal in ADHD brains.
This is the neurological explanation for why tasks feel impossible until they have a deadline, why ADHD people can hyperfocus on genuinely interesting work but can't start something routine. The reward signal is too weak to trigger engagement unless the task provides substantial dopamine input through novelty, urgency, or personal interest.
Stimulant medications work by increasing dopamine availability. This isn't giving the ADHD brain an unfair advantage -- it's restoring it closer to the baseline that neurotypical brains operate at naturally. For more on this mechanism, see our guide to ADHD and dopamine deficits.
Difference 3: Default Mode Network Suppression
The default mode network (DMN) is the brain's "resting state" -- a network active during mind-wandering, self-referential thinking, and daydreaming. In neurotypical brains, the DMN quiets down when a task requires focused attention. The cognitive control network takes over, and the mind stays on task.
In ADHD brains, this suppression is impaired. The DMN fails to quiet when it should, competing with attentional networks rather than standing down. This is the neurological basis of mind-wandering during tasks, internal distraction, and the sense that the brain is "hijacked" mid-task by unrelated thoughts.
Research using fMRI has shown that the degree of DMN suppression failure correlates with symptom severity in ADHD. The more the DMN stays active during tasks, the more attention problems are reported. This finding also explains why high-stimulation environments (noise, visual complexity, interesting context) can paradoxically help some ADHD people -- the external stimulation competes with the wandering DMN and keeps executive networks more engaged.
Difference 4: Smaller Basal Ganglia and Cerebellum
Multiple neuroimaging studies have identified reduced volume in the basal ganglia, particularly the caudate nucleus, in people with ADHD. The basal ganglia play a central role in motor control, procedural learning, and the selection of actions based on past experience -- in short, habit formation and automatic behavior.
When the basal ganglia are underactive, things that should become automatic -- routines, habits, social scripts -- require more conscious effort. This is why maintaining consistent habits is disproportionately hard for people with ADHD. The brain region that normally automates those behaviors runs at a reduced capacity.
The cerebellum, which controls timing and motor coordination but also contributes to cognitive timing and attention shifting, also shows reduced volume in some ADHD neuroimaging studies. This may contribute to the time perception difficulties and "time blindness" that many people with ADHD experience acutely.
Difference 5: Altered Connectivity Between Networks
Beyond individual brain regions, the connections between regions -- measured via resting-state fMRI -- show meaningful differences in ADHD. The communication between the executive control network and regions involved in salience detection (which things to pay attention to) is weaker. The prefrontal cortex exerts less top-down control over automatic responses.
This altered connectivity helps explain why ADHD involves more than just attention problems. Emotional dysregulation, impulsivity, working memory failures, and difficulty shifting between tasks all trace back to this broad connectivity pattern. For more on the emotional side, see our deep-dive on emotional dysregulation in ADHD.
Importantly, some connectivity differences become less pronounced with age and treatment, suggesting the brain retains meaningful plasticity in these networks.
Difference 6: Norepinephrine and the Arousal System
The ADHD brain also shows differences in norepinephrine signaling, particularly in the locus coeruleus -- the brain's main source of norepinephrine, which regulates arousal, alertness, and the ability to filter relevant from irrelevant input.
In neurotypical brains, optimal norepinephrine levels create a state of focused alertness. Too little produces inattention and difficulty filtering noise. The ADHD brain tends to run at suboptimal norepinephrine levels under ordinary conditions, which is why non-stimulant ADHD medications like atomoxetine and guanfacine target the norepinephrine system rather than dopamine directly.
This also explains why ADHD brains struggle with tasks in quiet environments. Without adequate arousal signal, the brain doesn't distinguish important from unimportant stimuli well. External stimulation -- noise, movement, a change of scene -- can paradoxically improve focus by raising arousal to a more functional level.
What This Means for Daily Life
Understanding the structural and chemical differences in the ADHD brain matters because it points toward strategies that actually work. Trying harder at the things the brain does poorly generates frustration and failure. Working with the brain's profile gets results.
One of the most practical implications involves scheduling. The ADHD brain has a narrower window of peak dopamine and norepinephrine availability -- typically shorter and less predictable than neurotypical brains. Stacking demanding cognitive work into that window and protecting it from interruption produces significantly better outcomes than spreading work evenly across the day.
Lifestack automates this by scheduling tasks based on your energy pattern rather than calendar slots. It places high-focus work in your peak window, low-demand tasks when you're running on fumes. For a brain that can't reliably perform this optimization manually -- because the PFC is busy just managing moment-to-moment demands -- an external system that does it automatically is not a luxury. It's compensation for a real structural difference.
Combined with consistent sleep, exercise, and an ADHD morning routine, energy-aware scheduling gives the ADHD brain the external scaffolding that the neurotypical brain handles internally.
Best Tool for Supporting the ADHD Brain
The structural differences in the ADHD brain don't disappear, but they can be compensated for with the right systems. Lifestack is built for exactly this: its energy-aware AI scheduler compensates for the ADHD brain's impaired self-scheduling ability by automatically placing tasks where they're most likely to get done.
Where the neurotypical brain can intuitively sequence a workday, the ADHD brain often stalls at exactly that planning step. Lifestack removes the step entirely -- giving you a ready schedule that accounts for deadlines, energy, and priority so you can get into work instead of preparing to work. At $7/month or $50/year with a 7-day free trial, it's one of the most focused ADHD-aligned planning tools available.
Frequently Asked Questions
What is the main difference between the ADHD brain and a normal brain?
The most consistently documented differences are: reduced prefrontal cortex volume and maturation, lower dopamine receptor density, impaired default mode network suppression during tasks, and reduced basal ganglia volume. These together produce the attention, motivation, and impulse control difficulties characteristic of ADHD.
Does the ADHD brain look different on a scan?
Yes, in group studies. MRI and fMRI studies consistently find structural and connectivity differences in ADHD brains compared to neurotypical controls. Individual scans aren't diagnostic -- the differences show up at the population level, not reliably enough to diagnose a single person from a scan alone.
Do ADHD brain differences go away in adulthood?
Not entirely. The prefrontal cortex continues maturing through the mid-20s, and some differences become less pronounced. But core structural differences in the basal ganglia, dopamine system, and connectivity patterns persist into adulthood. Approximately 60-75% of children with ADHD continue to meet diagnostic criteria as adults.
Is the ADHD brain smarter or more creative?
The ADHD brain is not uniformly smarter or more creative -- it's differently wired. Some ADHD traits (divergent thinking, high curiosity, hyperfocus capacity) can support creativity. Others (working memory deficits, attention regulation) can impair it. The relationship varies by individual and domain.
What helps the ADHD brain function better?
A combination of medication (stimulants or non-stimulants targeting dopamine and norepinephrine), behavioral strategies, adequate sleep, focus strategies, and external structure. Tools that compensate for planning and self-organization deficits -- like energy-aware schedulers -- directly address the functional gaps created by prefrontal and basal ganglia differences.
Can the ADHD brain change with treatment?
Yes. Stimulant medication produces measurable changes in prefrontal activity and connectivity during treatment. Long-term behavioral interventions and CBT for ADHD also support neuroplastic adaptation. The brain doesn't become neurotypical, but it adapts to use available capacity more effectively.



FOLLOW ON
FOLLOW ON
FOLLOW ON


Copyright 2026 © Lifestack. All rights reserved
Copyright 2026 © Lifestack. All rights reserved

