
Tips
Hyposomnia vs Hypersomnia: What's the Difference?
Hyposomnia vs Hypersomnia: What's the Difference?

Sleep problems come in many forms, but two terms that often cause confusion are hyposomnia and hypersomnia. Despite sounding similar, they describe opposite ends of the sleep spectrum: one means getting too little, the other too much.
Hyposomnia refers to sleeping fewer hours than your body needs, typically under six hours a night on a chronic basis. Hypersomnia is characterized by excessive sleep, with people sleeping 10 or more hours yet still feeling unrefreshed and drowsy throughout the day. Understanding which condition you might be dealing with is the first step toward addressing it.
Both conditions affect millions of people worldwide and can significantly impact daily functioning, mood, and cognitive performance. Sleep deprivation from hyposomnia accumulates as sleep debt, while hypersomnia can signal underlying medical or neurological conditions that need attention.
This guide breaks down the definitions, symptoms, causes, and treatment options for each, and explains what you can do to support healthier sleep patterns. If you have been wondering whether you might have the opposite of insomnia, this is the place to start.
Key Takeaways
Hyposomnia means insufficient sleep (under 6 hours); hypersomnia means excessive sleep (10+ hours with persistent daytime drowsiness)
Both conditions impair cognitive function, mood, and energy, but their root causes and treatment approaches differ substantially
Managing either condition starts with consistent sleep timing, professional evaluation, and energy-aware daily scheduling
What is Hyposomnia?
Hyposomnia is the medical term for sleeping significantly less than the recommended amount, typically defined as fewer than six hours per night on a regular basis. Unlike insomnia, where the problem is the inability to sleep even when given the opportunity, hyposomnia often involves voluntarily shortened sleep due to lifestyle demands, work schedules, or social pressures.
People with hyposomnia may fall asleep easily but simply do not spend enough time sleeping. The effects accumulate over time as sleep debt builds. Even mild sleep restriction below seven hours starts to degrade cognitive performance, reaction time, and mood within days.
Common triggers include shift work, late-night screen use, irregular schedules, stress, and anxiety. Some individuals are genetically predisposed to needing less sleep, but true short sleepers who thrive on five hours are extremely rare.
Symptoms of Hyposomnia
Persistent fatigue and tiredness throughout the day
Difficulty concentrating and reduced working memory
Irritability, mood swings, or emotional dysregulation
Increased appetite, especially for high-calorie foods
Slower reaction times and reduced alertness
Greater susceptibility to illness due to immune suppression
What is Hypersomnia?
Hypersomnia is the opposite problem. People with hypersomnia sleep for extended periods, often ten to twelve hours or more, and still experience profound daytime sleepiness. The sleep does not feel restorative, and napping during the day rarely provides lasting relief.
There are two main types. Primary hypersomnia arises without another underlying condition and includes disorders like narcolepsy and idiopathic hypersomnia. Secondary hypersomnia occurs as a symptom of another condition, such as sleep apnea, depression, thyroid disorders, or medication side effects.
One important distinction from hyposomnia is that people with hypersomnia often cannot control their sleep behavior through willpower alone. The urge to sleep is difficult to resist, even in inappropriate settings.
Symptoms of Hypersomnia
Sleeping 10 or more hours and still waking up tired
Difficulty waking up or disorientation upon waking (severe sleep inertia)
Involuntary napping throughout the day
Cognitive fog, slow thinking, and memory difficulties
Low motivation and persistent low mood
Automatic behavior, where tasks are performed without full awareness
Hyposomnia vs Hypersomnia: Key Differences
The clearest way to distinguish the two conditions is by how they manifest day to day.
With hyposomnia, the problem is duration: not enough hours are being slept. With hypersomnia, duration is often excessive yet quality is poor, or the biological need for sleep is far greater than normal. Both lead to daytime impairment, but for different reasons.
Sleep duration: Hyposomnia involves under 6 hours; hypersomnia involves 10+ hours
Daytime sleepiness: Hyposomnia causes fatigue from sleep debt; hypersomnia involves an uncontrollable sleep drive regardless of total hours
Wake difficulty: Hyposomnia sufferers generally wake on schedule but feel tired; hypersomnia often involves extreme difficulty leaving bed
Cause structure: Hyposomnia is often behavioral or lifestyle-driven; hypersomnia more frequently has neurological, medical, or psychiatric roots
Napping relief: A short nap may reduce hyposomnia fatigue; napping in hypersomnia often provides minimal benefit
Causes of Hyposomnia
Hyposomnia is most often a behavioral condition driven by choices or circumstances that cut sleep short.
Work schedules are a primary driver. Night shift workers, early-morning commuters, and people in high-demand roles frequently sacrifice sleep to meet demands. Social and cultural pressures around productivity, combined with late-night screens and entertainment, make insufficient sleep more common than ever.
Psychological factors play a large role too. Stress keeps the body's arousal system activated at night, making it harder to wind down. Anxiety, depression, and rumination all contribute to shortened sleep cycles. For people with ADHD, managing sleep timing is a particular challenge. Read our guide to ADHD sleep tips to see how neurodivergent individuals can protect their rest.
Less commonly, hyposomnia may relate to chronic pain, certain stimulant medications, or underlying sleep disorders that fragment sleep architecture even when time in bed is adequate.
Causes of Hypersomnia
Hypersomnia usually has a medical or neurological basis, which is why professional evaluation matters more here than with hyposomnia.
Narcolepsy is among the most recognized primary causes: a neurological disorder affecting the brain's ability to regulate the sleep-wake cycle. Idiopathic hypersomnia is another primary form with no identifiable cause, where the brain appears to generate an abnormally high sleep drive.
Secondary causes include untreated sleep apnea (where frequent breathing interruptions prevent deep sleep, prompting compensatory oversleeping), clinical depression, hypothyroidism, anemia, and autoimmune conditions. Certain medications, including antihistamines, some antidepressants, and antipsychotics, can also trigger hypersomnia as a side effect.
Genetic factors appear to contribute to several hypersomnia conditions, and research points to dysfunction in histamine or hypocretin signaling pathways as an underlying mechanism in primary forms. See our deeper breakdown of causes of excessive sleep and tiredness for a full clinical overview.
Treatment Approaches
For hyposomnia, behavioral interventions are usually the first step. Consistent bed and wake times, reducing screen light before bed, and limiting caffeine in the afternoon address the lifestyle root causes for many people. Our sleep hygiene guide covers these adjustments in detail.
Cognitive behavioral therapy for insomnia (CBT-I) includes sleep restriction, which temporarily limits time in bed to consolidate sleep drive and rebuild a healthy pattern. Addressing underlying stress or anxiety often produces meaningful improvements on its own.
Hypersomnia treatment is more varied and condition-dependent. When a secondary cause such as sleep apnea or thyroid dysfunction is identified, treating that root condition usually resolves the excessive sleepiness. Primary hypersomnia and narcolepsy are typically managed with stimulant medications, sodium oxybate, or newer agents like pitolisant and solriamfetol.
Lifestyle adjustments help in both conditions. Scheduled naps of 10 to 20 minutes, regular exercise, and consistent morning light exposure can help regulate circadian rhythms regardless of which condition is present. If you wake feeling unrefreshed consistently, a sleep study is the most reliable diagnostic step.
How Your Daily Schedule Affects Either Condition
Sleep problems do not exist in isolation. The timing and structure of your daily activities send powerful signals to your circadian system, either reinforcing healthy sleep or disrupting it.
People with hyposomnia often operate in a state of energy deficit without realizing how much their performance is degraded. Scheduling demanding cognitive work in the afternoon, when energy is already depleted, compounds the toll. Those with hypersomnia face the opposite problem: fighting excessive drowsiness during periods when work is unavoidable.
Energy-aware scheduling means organizing your day around your actual energy levels rather than fixed time blocks. If your body has a predictable low-energy window mid-afternoon, protecting that slot for lower-stakes tasks protects your output without fighting your biology. Learn why energy-based planning outperforms time blocking for most people.
For people dealing with sleep disruption related to ADHD, the challenge of maintaining a consistent schedule is compounded by circadian irregularities. Understanding ADHD and circadian rhythm can clarify why conventional sleep advice sometimes falls short for neurodivergent people.
Best Tool for Managing Sleep-Related Fatigue
Whether you are dealing with hyposomnia or hypersomnia, one of the most practical steps is aligning your work with your real energy levels.
Lifestack reads your sleep data, recovery patterns, and focus windows, then builds a daily schedule that puts demanding tasks in your high-energy windows and lighter work in recovery periods. Rather than imposing a fixed template, it adapts to what your body is actually capable of each day.
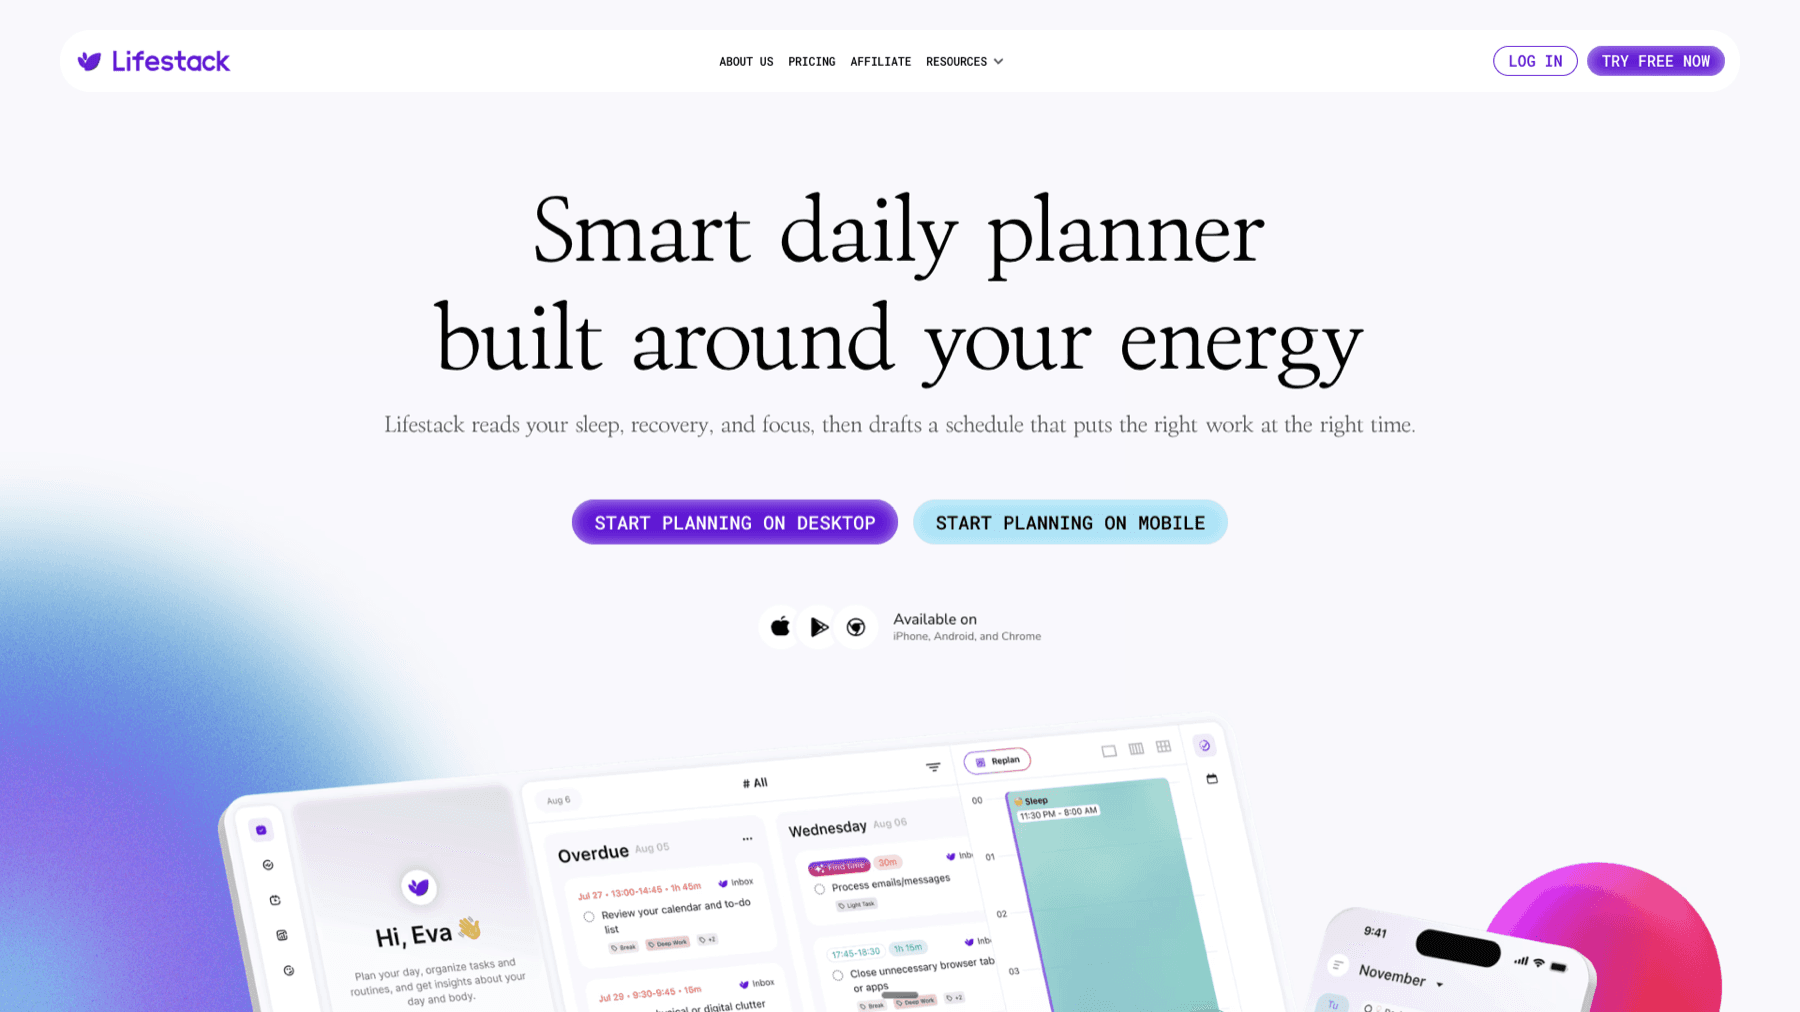
This matters most when sleep is unreliable. After a poor night, Lifestack reduces cognitive load in the schedule. After good recovery, it opens up capacity for deeper work. Pricing starts at $49.99 per year (7-day free trial) or $120 as a one-time lifetime purchase.
Learn more about how Lifestack was built around your energy.
Frequently Asked Questions
Is hyposomnia the same as insomnia?
No. Insomnia specifically involves difficulty falling or staying asleep despite adequate opportunity. Hyposomnia is about total sleep duration being insufficient, often due to behavioral choices or lifestyle constraints rather than a biological inability to sleep.
How many hours of sleep count as hypersomnia?
Regularly sleeping 10 or more hours per night combined with persistent daytime sleepiness is the general clinical threshold. Spending more than 10 hours in bed plus extended daytime napping, all while still feeling tired, warrants evaluation.
Can you have both hyposomnia and hypersomnia?
Some people experience cycles of sleep deprivation followed by compensatory oversleeping, which can resemble both conditions at different times. True co-occurrence of primary forms of both disorders is rare, and accurate diagnosis requires a sleep study or clinical evaluation.
What is the fastest way to recover from hyposomnia?
Gradually extending sleep by going to bed 30 minutes earlier each night, combined with reducing stimulant use in the afternoon and lowering evening light exposure, tends to produce the most sustainable recovery. Catching up in large chunks on weekends provides partial benefit but does not fully reverse accumulated sleep debt. Read how to fix your sleep schedule quickly for a step-by-step approach.
Is sleeping 10 hours bad?
Not always. Some people genuinely need more than 9 hours, particularly adolescents, athletes, or people recovering from illness. The concern arises when 10-plus hours is accompanied by daytime drowsiness that does not resolve, or when the pattern emerges suddenly without a clear cause, which may signal an underlying condition worth investigating.
Can hypersomnia cause depression, or does depression cause hypersomnia?
Both relationships exist. Depression commonly produces hypersomnia as a symptom, particularly in atypical depression. At the same time, persistent hypersomnia can contribute to low mood and reduced motivation. The two conditions often need to be addressed together for either to improve meaningfully.
Sleep problems come in many forms, but two terms that often cause confusion are hyposomnia and hypersomnia. Despite sounding similar, they describe opposite ends of the sleep spectrum: one means getting too little, the other too much.
Hyposomnia refers to sleeping fewer hours than your body needs, typically under six hours a night on a chronic basis. Hypersomnia is characterized by excessive sleep, with people sleeping 10 or more hours yet still feeling unrefreshed and drowsy throughout the day. Understanding which condition you might be dealing with is the first step toward addressing it.
Both conditions affect millions of people worldwide and can significantly impact daily functioning, mood, and cognitive performance. Sleep deprivation from hyposomnia accumulates as sleep debt, while hypersomnia can signal underlying medical or neurological conditions that need attention.
This guide breaks down the definitions, symptoms, causes, and treatment options for each, and explains what you can do to support healthier sleep patterns. If you have been wondering whether you might have the opposite of insomnia, this is the place to start.
Key Takeaways
Hyposomnia means insufficient sleep (under 6 hours); hypersomnia means excessive sleep (10+ hours with persistent daytime drowsiness)
Both conditions impair cognitive function, mood, and energy, but their root causes and treatment approaches differ substantially
Managing either condition starts with consistent sleep timing, professional evaluation, and energy-aware daily scheduling
What is Hyposomnia?
Hyposomnia is the medical term for sleeping significantly less than the recommended amount, typically defined as fewer than six hours per night on a regular basis. Unlike insomnia, where the problem is the inability to sleep even when given the opportunity, hyposomnia often involves voluntarily shortened sleep due to lifestyle demands, work schedules, or social pressures.
People with hyposomnia may fall asleep easily but simply do not spend enough time sleeping. The effects accumulate over time as sleep debt builds. Even mild sleep restriction below seven hours starts to degrade cognitive performance, reaction time, and mood within days.
Common triggers include shift work, late-night screen use, irregular schedules, stress, and anxiety. Some individuals are genetically predisposed to needing less sleep, but true short sleepers who thrive on five hours are extremely rare.
Symptoms of Hyposomnia
Persistent fatigue and tiredness throughout the day
Difficulty concentrating and reduced working memory
Irritability, mood swings, or emotional dysregulation
Increased appetite, especially for high-calorie foods
Slower reaction times and reduced alertness
Greater susceptibility to illness due to immune suppression
What is Hypersomnia?
Hypersomnia is the opposite problem. People with hypersomnia sleep for extended periods, often ten to twelve hours or more, and still experience profound daytime sleepiness. The sleep does not feel restorative, and napping during the day rarely provides lasting relief.
There are two main types. Primary hypersomnia arises without another underlying condition and includes disorders like narcolepsy and idiopathic hypersomnia. Secondary hypersomnia occurs as a symptom of another condition, such as sleep apnea, depression, thyroid disorders, or medication side effects.
One important distinction from hyposomnia is that people with hypersomnia often cannot control their sleep behavior through willpower alone. The urge to sleep is difficult to resist, even in inappropriate settings.
Symptoms of Hypersomnia
Sleeping 10 or more hours and still waking up tired
Difficulty waking up or disorientation upon waking (severe sleep inertia)
Involuntary napping throughout the day
Cognitive fog, slow thinking, and memory difficulties
Low motivation and persistent low mood
Automatic behavior, where tasks are performed without full awareness
Hyposomnia vs Hypersomnia: Key Differences
The clearest way to distinguish the two conditions is by how they manifest day to day.
With hyposomnia, the problem is duration: not enough hours are being slept. With hypersomnia, duration is often excessive yet quality is poor, or the biological need for sleep is far greater than normal. Both lead to daytime impairment, but for different reasons.
Sleep duration: Hyposomnia involves under 6 hours; hypersomnia involves 10+ hours
Daytime sleepiness: Hyposomnia causes fatigue from sleep debt; hypersomnia involves an uncontrollable sleep drive regardless of total hours
Wake difficulty: Hyposomnia sufferers generally wake on schedule but feel tired; hypersomnia often involves extreme difficulty leaving bed
Cause structure: Hyposomnia is often behavioral or lifestyle-driven; hypersomnia more frequently has neurological, medical, or psychiatric roots
Napping relief: A short nap may reduce hyposomnia fatigue; napping in hypersomnia often provides minimal benefit
Causes of Hyposomnia
Hyposomnia is most often a behavioral condition driven by choices or circumstances that cut sleep short.
Work schedules are a primary driver. Night shift workers, early-morning commuters, and people in high-demand roles frequently sacrifice sleep to meet demands. Social and cultural pressures around productivity, combined with late-night screens and entertainment, make insufficient sleep more common than ever.
Psychological factors play a large role too. Stress keeps the body's arousal system activated at night, making it harder to wind down. Anxiety, depression, and rumination all contribute to shortened sleep cycles. For people with ADHD, managing sleep timing is a particular challenge. Read our guide to ADHD sleep tips to see how neurodivergent individuals can protect their rest.
Less commonly, hyposomnia may relate to chronic pain, certain stimulant medications, or underlying sleep disorders that fragment sleep architecture even when time in bed is adequate.
Causes of Hypersomnia
Hypersomnia usually has a medical or neurological basis, which is why professional evaluation matters more here than with hyposomnia.
Narcolepsy is among the most recognized primary causes: a neurological disorder affecting the brain's ability to regulate the sleep-wake cycle. Idiopathic hypersomnia is another primary form with no identifiable cause, where the brain appears to generate an abnormally high sleep drive.
Secondary causes include untreated sleep apnea (where frequent breathing interruptions prevent deep sleep, prompting compensatory oversleeping), clinical depression, hypothyroidism, anemia, and autoimmune conditions. Certain medications, including antihistamines, some antidepressants, and antipsychotics, can also trigger hypersomnia as a side effect.
Genetic factors appear to contribute to several hypersomnia conditions, and research points to dysfunction in histamine or hypocretin signaling pathways as an underlying mechanism in primary forms. See our deeper breakdown of causes of excessive sleep and tiredness for a full clinical overview.
Treatment Approaches
For hyposomnia, behavioral interventions are usually the first step. Consistent bed and wake times, reducing screen light before bed, and limiting caffeine in the afternoon address the lifestyle root causes for many people. Our sleep hygiene guide covers these adjustments in detail.
Cognitive behavioral therapy for insomnia (CBT-I) includes sleep restriction, which temporarily limits time in bed to consolidate sleep drive and rebuild a healthy pattern. Addressing underlying stress or anxiety often produces meaningful improvements on its own.
Hypersomnia treatment is more varied and condition-dependent. When a secondary cause such as sleep apnea or thyroid dysfunction is identified, treating that root condition usually resolves the excessive sleepiness. Primary hypersomnia and narcolepsy are typically managed with stimulant medications, sodium oxybate, or newer agents like pitolisant and solriamfetol.
Lifestyle adjustments help in both conditions. Scheduled naps of 10 to 20 minutes, regular exercise, and consistent morning light exposure can help regulate circadian rhythms regardless of which condition is present. If you wake feeling unrefreshed consistently, a sleep study is the most reliable diagnostic step.
How Your Daily Schedule Affects Either Condition
Sleep problems do not exist in isolation. The timing and structure of your daily activities send powerful signals to your circadian system, either reinforcing healthy sleep or disrupting it.
People with hyposomnia often operate in a state of energy deficit without realizing how much their performance is degraded. Scheduling demanding cognitive work in the afternoon, when energy is already depleted, compounds the toll. Those with hypersomnia face the opposite problem: fighting excessive drowsiness during periods when work is unavoidable.
Energy-aware scheduling means organizing your day around your actual energy levels rather than fixed time blocks. If your body has a predictable low-energy window mid-afternoon, protecting that slot for lower-stakes tasks protects your output without fighting your biology. Learn why energy-based planning outperforms time blocking for most people.
For people dealing with sleep disruption related to ADHD, the challenge of maintaining a consistent schedule is compounded by circadian irregularities. Understanding ADHD and circadian rhythm can clarify why conventional sleep advice sometimes falls short for neurodivergent people.
Best Tool for Managing Sleep-Related Fatigue
Whether you are dealing with hyposomnia or hypersomnia, one of the most practical steps is aligning your work with your real energy levels.
Lifestack reads your sleep data, recovery patterns, and focus windows, then builds a daily schedule that puts demanding tasks in your high-energy windows and lighter work in recovery periods. Rather than imposing a fixed template, it adapts to what your body is actually capable of each day.
This matters most when sleep is unreliable. After a poor night, Lifestack reduces cognitive load in the schedule. After good recovery, it opens up capacity for deeper work. Pricing starts at $49.99 per year (7-day free trial) or $120 as a one-time lifetime purchase.
Learn more about how Lifestack was built around your energy.
Frequently Asked Questions
Is hyposomnia the same as insomnia?
No. Insomnia specifically involves difficulty falling or staying asleep despite adequate opportunity. Hyposomnia is about total sleep duration being insufficient, often due to behavioral choices or lifestyle constraints rather than a biological inability to sleep.
How many hours of sleep count as hypersomnia?
Regularly sleeping 10 or more hours per night combined with persistent daytime sleepiness is the general clinical threshold. Spending more than 10 hours in bed plus extended daytime napping, all while still feeling tired, warrants evaluation.
Can you have both hyposomnia and hypersomnia?
Some people experience cycles of sleep deprivation followed by compensatory oversleeping, which can resemble both conditions at different times. True co-occurrence of primary forms of both disorders is rare, and accurate diagnosis requires a sleep study or clinical evaluation.
What is the fastest way to recover from hyposomnia?
Gradually extending sleep by going to bed 30 minutes earlier each night, combined with reducing stimulant use in the afternoon and lowering evening light exposure, tends to produce the most sustainable recovery. Catching up in large chunks on weekends provides partial benefit but does not fully reverse accumulated sleep debt. Read how to fix your sleep schedule quickly for a step-by-step approach.
Is sleeping 10 hours bad?
Not always. Some people genuinely need more than 9 hours, particularly adolescents, athletes, or people recovering from illness. The concern arises when 10-plus hours is accompanied by daytime drowsiness that does not resolve, or when the pattern emerges suddenly without a clear cause, which may signal an underlying condition worth investigating.
Can hypersomnia cause depression, or does depression cause hypersomnia?
Both relationships exist. Depression commonly produces hypersomnia as a symptom, particularly in atypical depression. At the same time, persistent hypersomnia can contribute to low mood and reduced motivation. The two conditions often need to be addressed together for either to improve meaningfully.



FOLLOW ON
FOLLOW ON
FOLLOW ON


Copyright 2026 © Lifestack. All rights reserved
Copyright 2026 © Lifestack. All rights reserved

