
Tips
ADHD or ADD: What's the Difference in 2026
ADHD or ADD: What's the Difference in 2026

ADD is a term a lot of people still use, but it hasn't been a medical diagnosis since 1994. If you've been told you have ADD, been diagnosed with ADHD, or are trying to understand which term applies to you, the short answer is this: they're the same condition, and modern clinical language uses ADHD for all presentations of it, including the ones without obvious hyperactivity.
The longer answer matters more. Because the terminology shift tracks a real change in how the condition is understood, and knowing where that change came from helps you make sense of your own diagnosis, find the right treatment, and talk to doctors and school systems with the right framing.
Key Takeaways
ADD is no longer a medical diagnosis. Since 1994, ADHD is the clinical term for all presentations of the condition, including the inattentive type that was previously called ADD.
The three current ADHD subtypes are: predominantly inattentive, predominantly hyperactive-impulsive, and combined type.
If you were diagnosed with ADD in the past, your condition now falls under the inattentive-type ADHD category in current diagnostic frameworks.
What ADD Was
Attention Deficit Disorder (ADD) was a diagnostic label used in the DSM-III, published in 1980. It described a condition characterized primarily by inattention, with two subtypes: ADD with hyperactivity and ADD without hyperactivity. The version without hyperactivity was what most people meant when they said "ADD" in casual use.
In 1987, the DSM-III-R collapsed these into a single diagnosis called Attention-Deficit Hyperactivity Disorder (ADHD), reflecting a growing understanding that the condition existed on a spectrum and that hyperactivity and inattention were more connected than the earlier framework acknowledged. The DSM-IV in 1994 refined this further, introducing the three-subtype structure that forms the basis of current diagnosis: predominantly inattentive, predominantly hyperactive-impulsive, and combined type.
ADD survived in popular use even after the clinical terminology moved on. Today, when someone says "I have ADD," they almost always mean they have the predominantly inattentive presentation of ADHD. No hyperactivity, or at least no obvious external hyperactivity. The condition is real and recognized. The label just isn't the one clinicians use.
The Three ADHD Subtypes Today
Predominantly inattentive type (formerly ADD): This presentation is defined by difficulty sustaining attention, forgetting everyday tasks, losing things, missing details, becoming easily distracted, and struggling to follow through on tasks. Time blindness is common. Hyperactivity, if present, tends to be internal, a restless mental quality rather than visible physical movement. This is the presentation most often missed in children, particularly girls, and most often diagnosed late in adulthood.
Predominantly hyperactive-impulsive type: Defined by fidgeting, difficulty staying seated, talking excessively, interrupting others, and acting before thinking. Inattention is less pronounced. This is what most people picture when they imagine "classic" ADHD, though it's actually less common in isolation than the combined type.
Combined type: The most common clinical presentation. Meets the threshold for both inattentive and hyperactive-impulsive symptoms. Most adults with ADHD who were diagnosed as children with the hyperactive type find that as they age, the visible hyperactivity decreases while inattentive symptoms remain. This often shifts their presentation toward the combined or inattentive type over time.
Why the Terminology Matters
It might seem like a labeling issue, but the terminology has practical consequences.
If you're seeking a diagnosis as an adult and you tell a clinician "I think I have ADD," you may or may not be using language they recognize, depending on when they trained. More importantly, the old ADD framing sometimes led to evaluations focused exclusively on attention, skipping the executive function, impulsivity, and working memory components that are now understood as central to inattentive ADHD. A proper evaluation per current standards captures the full picture. Our post on ADHD DSM-5 criteria breaks down the current diagnostic framework in detail.
The terminology also affects school accommodations and workplace support. If you're pursuing formal accommodations, having the correct current diagnosis terminology on paper matters. "ADD" may be treated as informal or outdated in some settings. "ADHD, predominantly inattentive type" is the current clinical language, and it's what opens access to legally supported accommodations.
Inattentive ADHD Symptoms (What Was Called ADD)
The DSM-5 lists nine inattentive symptoms. To meet the threshold for a predominantly inattentive diagnosis, adults need six or more present consistently across at least two settings (work, school, home):
Often fails to give close attention to details or makes careless mistakes
Often has difficulty sustaining attention during tasks or play
Often does not seem to listen when spoken to directly
Often fails to follow through on instructions and does not finish tasks
Often has difficulty organizing tasks and activities
Often avoids tasks that require sustained mental effort
Often loses things needed for tasks (keys, papers, tools)
Is often easily distracted by unrelated thoughts or stimuli
Is often forgetful in daily activities
These symptoms need to have been present before age 12, to have persisted for at least six months, and to cause impairment in functioning beyond what would be typical for someone's developmental level.
For a deeper look at what inattentive ADHD looks like in day-to-day life, see our guide on ADHD task paralysis and ADHD working memory.
Why Inattentive ADHD Gets Missed
The predominantly inattentive presentation is the most underdiagnosed subtype, especially in girls, women, and adults who developed strong coping mechanisms early on. Without the disruptive behavior that flags hyperactive-impulsive ADHD in classroom settings, inattentive ADHD often reads as laziness, low motivation, daydreaming, or lack of effort.
Girls are particularly affected. Research shows that girls with ADHD tend to show more inattentive symptoms and fewer externally disruptive ones, leading to lower rates of referral for evaluation. Many women are not diagnosed until adulthood, often after years of wondering why ordinary tasks require extraordinary effort. See our post on ADHD masking in women for more on this pattern.
Late diagnosis is common and valid. An adult diagnosis of ADHD, even if given as "inattentive type" rather than the "ADD" they grew up calling it, is no less meaningful or actionable.
Treatment Is the Same Regardless of Label
Whether someone is diagnosed with "ADHD, predominantly inattentive type" or was previously labeled with ADD, the treatment options are the same. Stimulant medications (amphetamine-based and methylphenidate-based) remain first-line. Non-stimulants are the alternative when stimulants aren't appropriate. Behavioral strategies, external structure, and environmental accommodations play a major role alongside medication.
Medication tends to be especially impactful for the inattentive presentation. It directly addresses the dopamine and norepinephrine dysregulation that drives attention, working memory, and task follow-through. See our full guide on medication for inattentive ADHD for a breakdown of what's available and how dosing decisions get made.
Building Daily Structure Alongside Diagnosis
A diagnosis, whether current ADHD terminology or old ADD framing, clarifies what you're working with. It doesn't automatically build the daily systems that help you function well.
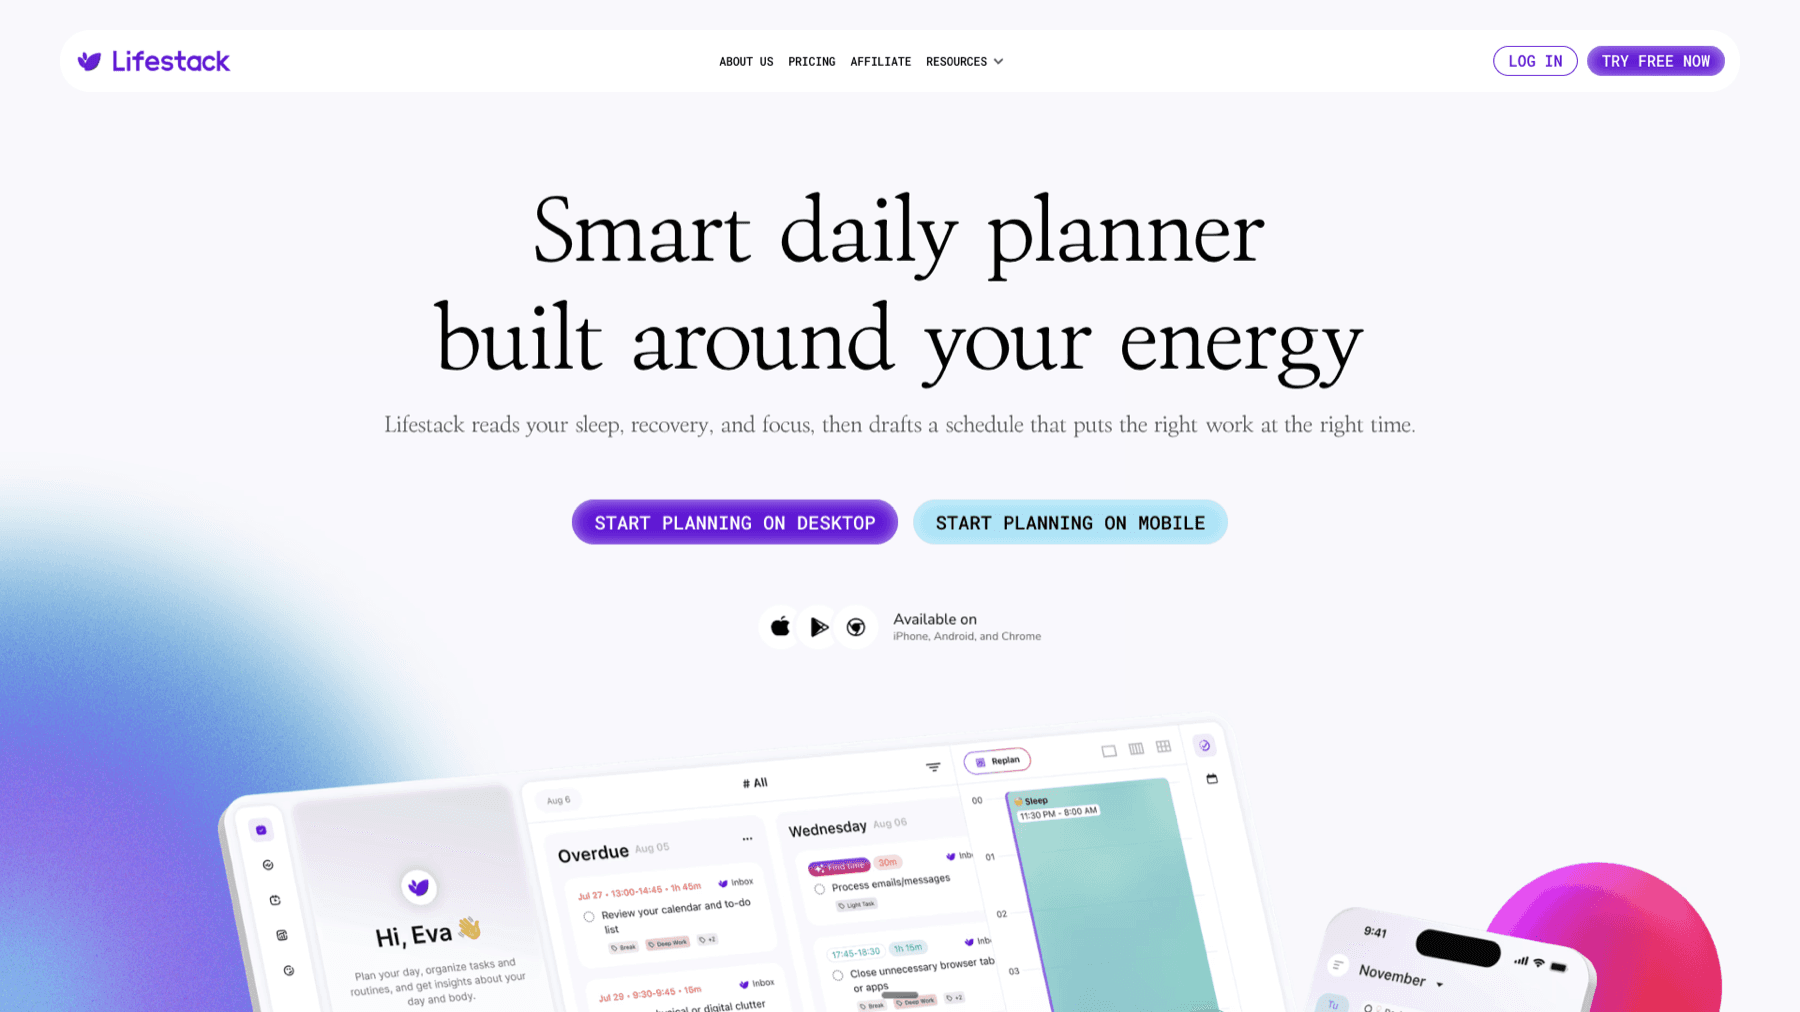
Lifestack is a planning and scheduling tool designed around how inattentive ADHD brains actually operate. Its energy-aware scheduling places tasks requiring sustained focus during your highest-capacity windows, and reduces the decision load of figuring out what to work on next, one of the areas where inattentive ADHD shows up most. It syncs with your existing calendars and costs $7/month or $50/year (with a 7-day free trial on the annual plan). Building a structured daily system on top of whatever treatment you're using is how the pieces fit together. Our guide on ADHD daily planner strategies covers this in more detail.
Best Tool for Inattentive ADHD Daily Management
For the executive function gaps that both the old ADD label and the current inattentive-type ADHD framework describe, Lifestack is the most directly relevant tool. Energy-aware scheduling, calendar integration, and AI-built daily plans address exactly what the diagnosis points to. The ADHD morning routine guide pairs well with it for building a consistent daily launch.
Frequently Asked Questions
Is ADD the same as ADHD?
ADD is an older term that is no longer used clinically. Since 1994, ADHD is the diagnosis for all presentations of the condition, including the inattentive type that was previously called ADD. Colloquially, people still use ADD to mean "ADHD without obvious hyperactivity," which is now called predominantly inattentive type ADHD.
Which is more common, ADD or ADHD?
These terms don't represent different conditions; they're old and new labels for the same one. Within the current ADHD framework, the combined type is the most common subtype in people who are clinically diagnosed, though the predominantly inattentive type may be underdiagnosed and potentially even more prevalent than current statistics reflect.
Can you have ADD without hyperactivity?
Yes, and this is what the predominantly inattentive type of ADHD describes. People with this presentation may have internal restlessness, racing thoughts, or a racing quality to their attention, but don't display the external physical hyperactivity associated with the hyperactive-impulsive subtype. The condition is real and often significantly impairing even without visible behavioral symptoms.
Does inattentive ADHD (formerly ADD) get treated differently?
The medication options are the same, though some prescribers note that dosing considerations for predominantly inattentive ADHD may skew slightly different since the primary targets are attention, working memory, and follow-through rather than impulse control and behavioral regulation. Behavioral strategies emphasize structure-building and task-initiation support, which align well with the inattentive presentation.
Why was ADD renamed to ADHD?
The rename reflects a better understanding of the condition. Research showed that hyperactivity and inattention were both part of a single disorder spectrum rather than separate conditions. Using one term, ADHD, for all presentations better captures the underlying neurology, while the three-subtype structure preserves the meaningful clinical distinctions between them.
ADD is a term a lot of people still use, but it hasn't been a medical diagnosis since 1994. If you've been told you have ADD, been diagnosed with ADHD, or are trying to understand which term applies to you, the short answer is this: they're the same condition, and modern clinical language uses ADHD for all presentations of it, including the ones without obvious hyperactivity.
The longer answer matters more. Because the terminology shift tracks a real change in how the condition is understood, and knowing where that change came from helps you make sense of your own diagnosis, find the right treatment, and talk to doctors and school systems with the right framing.
Key Takeaways
ADD is no longer a medical diagnosis. Since 1994, ADHD is the clinical term for all presentations of the condition, including the inattentive type that was previously called ADD.
The three current ADHD subtypes are: predominantly inattentive, predominantly hyperactive-impulsive, and combined type.
If you were diagnosed with ADD in the past, your condition now falls under the inattentive-type ADHD category in current diagnostic frameworks.
What ADD Was
Attention Deficit Disorder (ADD) was a diagnostic label used in the DSM-III, published in 1980. It described a condition characterized primarily by inattention, with two subtypes: ADD with hyperactivity and ADD without hyperactivity. The version without hyperactivity was what most people meant when they said "ADD" in casual use.
In 1987, the DSM-III-R collapsed these into a single diagnosis called Attention-Deficit Hyperactivity Disorder (ADHD), reflecting a growing understanding that the condition existed on a spectrum and that hyperactivity and inattention were more connected than the earlier framework acknowledged. The DSM-IV in 1994 refined this further, introducing the three-subtype structure that forms the basis of current diagnosis: predominantly inattentive, predominantly hyperactive-impulsive, and combined type.
ADD survived in popular use even after the clinical terminology moved on. Today, when someone says "I have ADD," they almost always mean they have the predominantly inattentive presentation of ADHD. No hyperactivity, or at least no obvious external hyperactivity. The condition is real and recognized. The label just isn't the one clinicians use.
The Three ADHD Subtypes Today
Predominantly inattentive type (formerly ADD): This presentation is defined by difficulty sustaining attention, forgetting everyday tasks, losing things, missing details, becoming easily distracted, and struggling to follow through on tasks. Time blindness is common. Hyperactivity, if present, tends to be internal, a restless mental quality rather than visible physical movement. This is the presentation most often missed in children, particularly girls, and most often diagnosed late in adulthood.
Predominantly hyperactive-impulsive type: Defined by fidgeting, difficulty staying seated, talking excessively, interrupting others, and acting before thinking. Inattention is less pronounced. This is what most people picture when they imagine "classic" ADHD, though it's actually less common in isolation than the combined type.
Combined type: The most common clinical presentation. Meets the threshold for both inattentive and hyperactive-impulsive symptoms. Most adults with ADHD who were diagnosed as children with the hyperactive type find that as they age, the visible hyperactivity decreases while inattentive symptoms remain. This often shifts their presentation toward the combined or inattentive type over time.
Why the Terminology Matters
It might seem like a labeling issue, but the terminology has practical consequences.
If you're seeking a diagnosis as an adult and you tell a clinician "I think I have ADD," you may or may not be using language they recognize, depending on when they trained. More importantly, the old ADD framing sometimes led to evaluations focused exclusively on attention, skipping the executive function, impulsivity, and working memory components that are now understood as central to inattentive ADHD. A proper evaluation per current standards captures the full picture. Our post on ADHD DSM-5 criteria breaks down the current diagnostic framework in detail.
The terminology also affects school accommodations and workplace support. If you're pursuing formal accommodations, having the correct current diagnosis terminology on paper matters. "ADD" may be treated as informal or outdated in some settings. "ADHD, predominantly inattentive type" is the current clinical language, and it's what opens access to legally supported accommodations.
Inattentive ADHD Symptoms (What Was Called ADD)
The DSM-5 lists nine inattentive symptoms. To meet the threshold for a predominantly inattentive diagnosis, adults need six or more present consistently across at least two settings (work, school, home):
Often fails to give close attention to details or makes careless mistakes
Often has difficulty sustaining attention during tasks or play
Often does not seem to listen when spoken to directly
Often fails to follow through on instructions and does not finish tasks
Often has difficulty organizing tasks and activities
Often avoids tasks that require sustained mental effort
Often loses things needed for tasks (keys, papers, tools)
Is often easily distracted by unrelated thoughts or stimuli
Is often forgetful in daily activities
These symptoms need to have been present before age 12, to have persisted for at least six months, and to cause impairment in functioning beyond what would be typical for someone's developmental level.
For a deeper look at what inattentive ADHD looks like in day-to-day life, see our guide on ADHD task paralysis and ADHD working memory.
Why Inattentive ADHD Gets Missed
The predominantly inattentive presentation is the most underdiagnosed subtype, especially in girls, women, and adults who developed strong coping mechanisms early on. Without the disruptive behavior that flags hyperactive-impulsive ADHD in classroom settings, inattentive ADHD often reads as laziness, low motivation, daydreaming, or lack of effort.
Girls are particularly affected. Research shows that girls with ADHD tend to show more inattentive symptoms and fewer externally disruptive ones, leading to lower rates of referral for evaluation. Many women are not diagnosed until adulthood, often after years of wondering why ordinary tasks require extraordinary effort. See our post on ADHD masking in women for more on this pattern.
Late diagnosis is common and valid. An adult diagnosis of ADHD, even if given as "inattentive type" rather than the "ADD" they grew up calling it, is no less meaningful or actionable.
Treatment Is the Same Regardless of Label
Whether someone is diagnosed with "ADHD, predominantly inattentive type" or was previously labeled with ADD, the treatment options are the same. Stimulant medications (amphetamine-based and methylphenidate-based) remain first-line. Non-stimulants are the alternative when stimulants aren't appropriate. Behavioral strategies, external structure, and environmental accommodations play a major role alongside medication.
Medication tends to be especially impactful for the inattentive presentation. It directly addresses the dopamine and norepinephrine dysregulation that drives attention, working memory, and task follow-through. See our full guide on medication for inattentive ADHD for a breakdown of what's available and how dosing decisions get made.
Building Daily Structure Alongside Diagnosis
A diagnosis, whether current ADHD terminology or old ADD framing, clarifies what you're working with. It doesn't automatically build the daily systems that help you function well.
Lifestack is a planning and scheduling tool designed around how inattentive ADHD brains actually operate. Its energy-aware scheduling places tasks requiring sustained focus during your highest-capacity windows, and reduces the decision load of figuring out what to work on next, one of the areas where inattentive ADHD shows up most. It syncs with your existing calendars and costs $7/month or $50/year (with a 7-day free trial on the annual plan). Building a structured daily system on top of whatever treatment you're using is how the pieces fit together. Our guide on ADHD daily planner strategies covers this in more detail.
Best Tool for Inattentive ADHD Daily Management
For the executive function gaps that both the old ADD label and the current inattentive-type ADHD framework describe, Lifestack is the most directly relevant tool. Energy-aware scheduling, calendar integration, and AI-built daily plans address exactly what the diagnosis points to. The ADHD morning routine guide pairs well with it for building a consistent daily launch.
Frequently Asked Questions
Is ADD the same as ADHD?
ADD is an older term that is no longer used clinically. Since 1994, ADHD is the diagnosis for all presentations of the condition, including the inattentive type that was previously called ADD. Colloquially, people still use ADD to mean "ADHD without obvious hyperactivity," which is now called predominantly inattentive type ADHD.
Which is more common, ADD or ADHD?
These terms don't represent different conditions; they're old and new labels for the same one. Within the current ADHD framework, the combined type is the most common subtype in people who are clinically diagnosed, though the predominantly inattentive type may be underdiagnosed and potentially even more prevalent than current statistics reflect.
Can you have ADD without hyperactivity?
Yes, and this is what the predominantly inattentive type of ADHD describes. People with this presentation may have internal restlessness, racing thoughts, or a racing quality to their attention, but don't display the external physical hyperactivity associated with the hyperactive-impulsive subtype. The condition is real and often significantly impairing even without visible behavioral symptoms.
Does inattentive ADHD (formerly ADD) get treated differently?
The medication options are the same, though some prescribers note that dosing considerations for predominantly inattentive ADHD may skew slightly different since the primary targets are attention, working memory, and follow-through rather than impulse control and behavioral regulation. Behavioral strategies emphasize structure-building and task-initiation support, which align well with the inattentive presentation.
Why was ADD renamed to ADHD?
The rename reflects a better understanding of the condition. Research showed that hyperactivity and inattention were both part of a single disorder spectrum rather than separate conditions. Using one term, ADHD, for all presentations better captures the underlying neurology, while the three-subtype structure preserves the meaningful clinical distinctions between them.



FOLLOW ON
FOLLOW ON
FOLLOW ON


Copyright 2026 © Lifestack. All rights reserved
Copyright 2026 © Lifestack. All rights reserved

